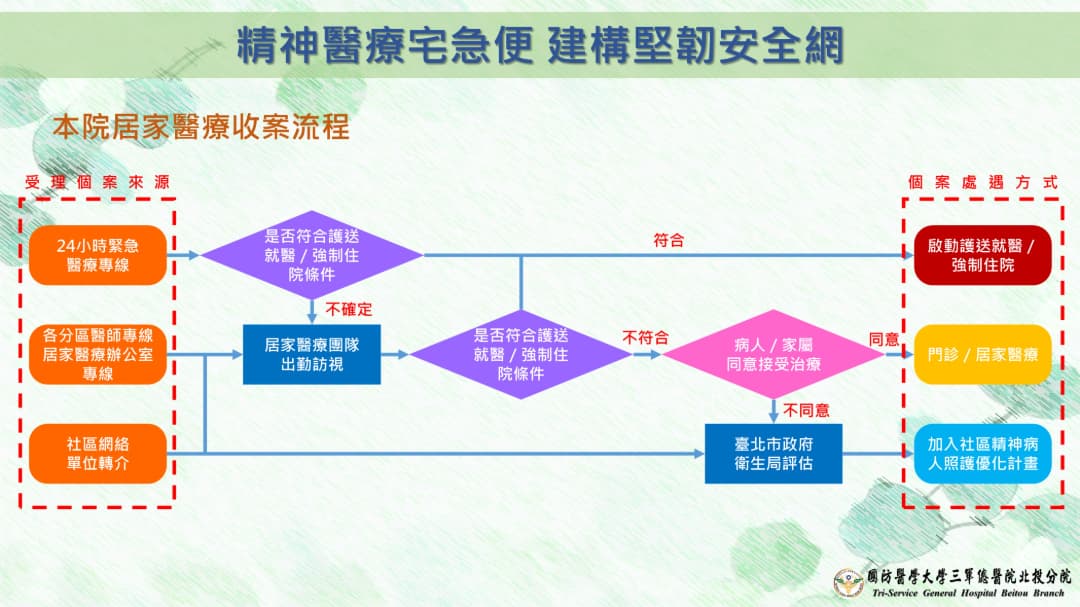
Provide early intervention and crisis management for individuals with suspected mental illness or community-dwelling psychiatric patients.
Deliver ongoing home-based psychiatric care for patients with mental illness who lack insight into their condition and are unwilling to seek medical treatment.
Conduct continuous follow-up and treatment for patients with severe mental illness after discharge from involuntary hospitalization.
Offer assessment and continuous care for homeless individuals through street-based psychiatric outreach services.
Our hospital’s Community Psychiatry Department is one of only four designated Community Psychiatry Specialty Training Hospitals nationwide. Our physicians serve as consultants to the Taipei City Government, members of Social Safety Net–related committees, and key leaders in the Community Psychiatry Association, and have contributed to domestic violence prevention training materials commissioned by the Ministry of Health and Welfare, demonstrating influence from clinical practice to policy development.
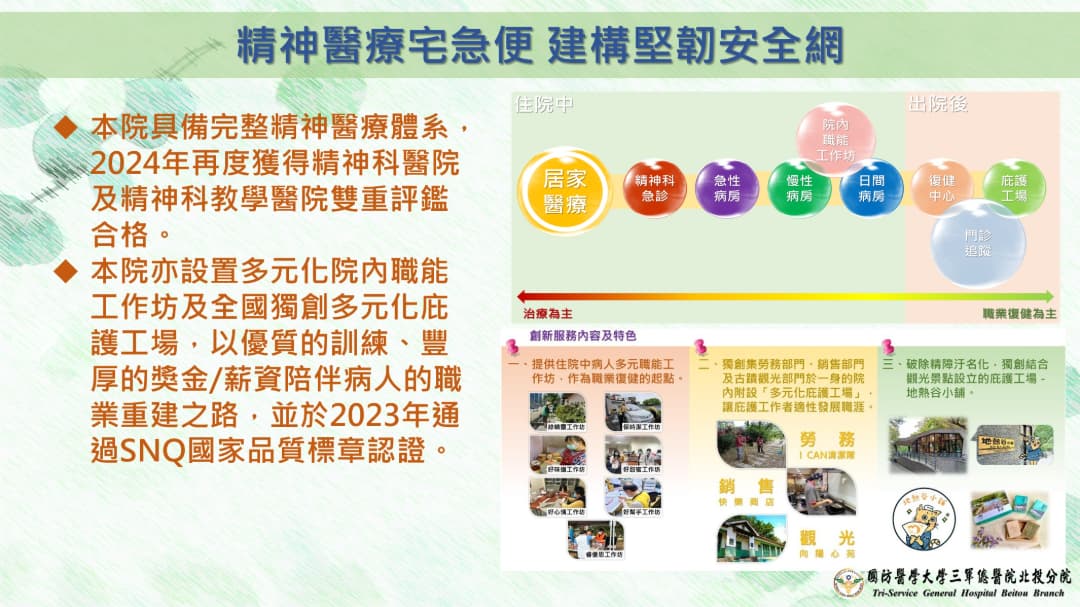
Our team delivers proactive outreach, timely intervention, and comprehensive care, and has operated Taipei City’s 24-hour Community Emergency Medical Response Program for over 26 years, covering 29 districts across Taipei and New Taipei City. Through close collaboration with law enforcement, social welfare, and public health agencies, we manage high-risk and socially sensitive cases. Integrated services—including community rehabilitation centers, an SNQ-recognized day hospital, and a sheltered workshop—provide a full continuum of care from acute treatment to vocational reintegration. We also pioneered an NGO-partnered street-based psychiatric outreach model, now expanded to New Taipei City and Taoyuan, demonstrating a scalable and sustainable community psychiatry care model.
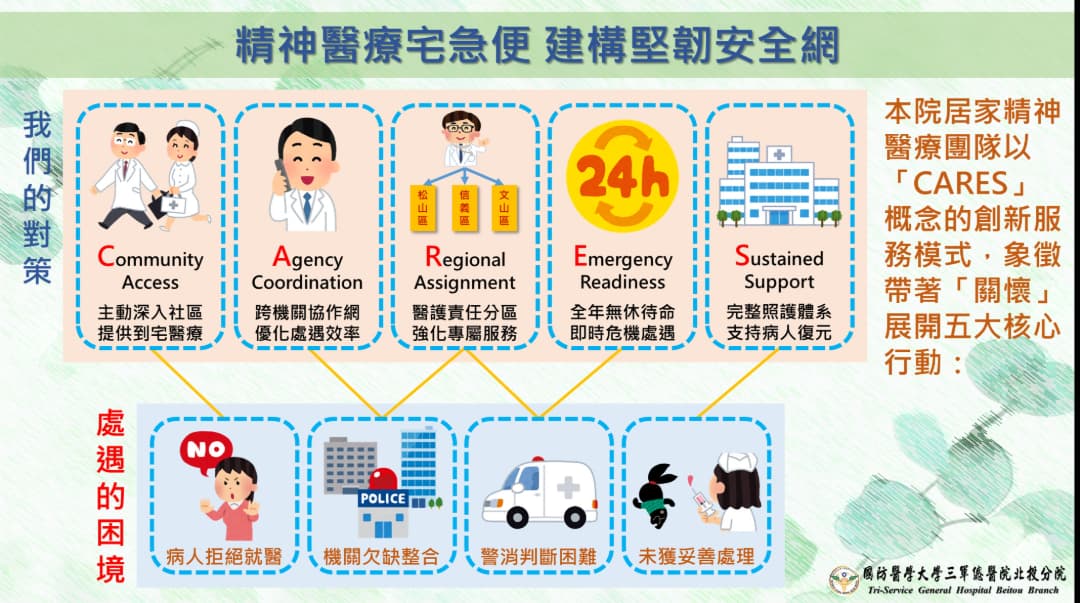
The hospital pioneered the CARES model, built on five key
actions:
Community Access – proactive outreach
Agency Coordination –cross-Agency Collaborative Network
Regional Assignment – physician accountability by area
Emergency Readiness – around-the-clock crisis response
Sustained Support – seamless care and rehabilitation
Psychiatric home-based medical services are provided by a team of 21 attending psychiatrists and 8 full-time psychiatric nurses.
The psychiatric home-based care program serves approximately 780–800 visits per month, exceeding 9,300 visits annually.
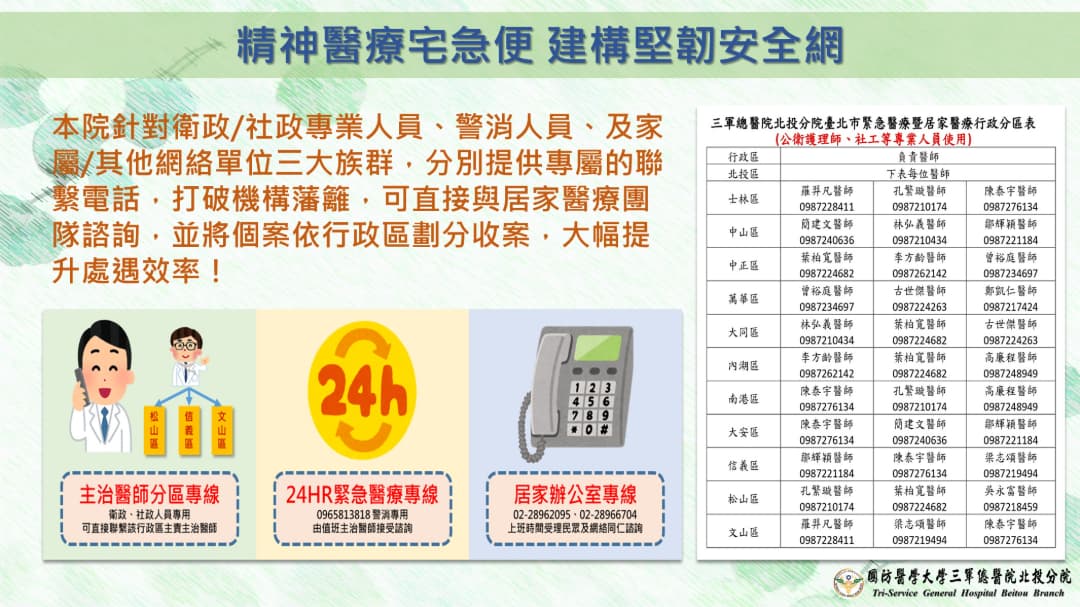
In each of Taipei City’s 12 administrative districts, at least three attending psychiatrists are assigned primary responsibility for emergency response and on-site psychiatric intervention.
The 24-hour community emergency psychiatric response service averages approximately 500 dispatches per year and has accounted for two-thirds of all such services in Taipei City for over a decade.
The rehospitalization rate of patients enrolled in home-based care within 1 to 3 years is below 4%.
The one-year rehospitalization rate following discharge from involuntary hospitalization is 18%.
The one-year follow-up rate for patients discharged from involuntary hospitalization who continued outpatient or home-based treatment at our hospital is 88%.
Among homeless individuals, 99.3% showed improvement in psychiatric symptoms, with an average symptom reduction of 57.4%.
The success rate of emergency dispatch and escorted medical transport is 100%.
There have been zero major adverse events in the home-based medical care program.
There have been zero injury incidents related to emergency dispatch operations.
Annual satisfaction and quality-of-life surveys for home-based medical care consistently score above 90 points (out of 100).
The average satisfaction score for the Care Optimization Program for Suspected or Community-Dwelling Psychiatric Patients is 4.3 (out of 5).
The average loss-to-follow-up rate in the Care Optimization Program for Suspected or Community-Dwelling Psychiatric Patients is 2.2%.
The average refusal rate in the Care Optimization Program for Suspected or Community-Dwelling Psychiatric Patients is 4.4%.
The 1–3 year rehospitalization rate for patients enrolled in home-based care is below 4%, substantially outperforming Germany’s rate of 31.12% (Bechdolf et al., 2024).
The one-year follow-up rate after discharge from involuntary hospitalization is 88%, exceeding those reported in Japan at 40.5% (Kikuchi et al., 2013) and the United Kingdom at 51.9% (O’Donoghue et al., 2015).
The one-year rehospitalization rate after discharge from involuntary hospitalization is 18%, lower than rates reported in Japan (24–43%; Kikuchi et al., 2013) and Switzerland (34.2%; Hofmann et al., 2022).
Among homeless individuals, psychiatric symptoms improved by an average of 57.4%, surpassing the 26% improvement reported in Germany (Coldwell et al., 2007).
Establish a seamless continuum of care from acute psychiatric intervention to occupational rehabilitation to enhance the quality of care.
Implement multi-pronged, cross-network collaboration, utilizing dedicated hotlines for three key populations and interagency LINE groups to improve response efficiency.
Provide 24-hour rapid response and proactive outreach to reduce rehospitalization rates and mitigate community crises.
Integrate NGO-partnered street-based psychiatric outreach to effectively intervene with homeless individuals with severe mental illness.
Develop a replicable community psychiatry care model to strengthen continuity of care and reinforce the social safety net.