Artificial intelligence model using Routine Blood Tests and Cellular Population Data to Predict the Risk of Bacteremia in Patients
Adult patients with suspected bacterial infections in the emergency department or during hospitalization.
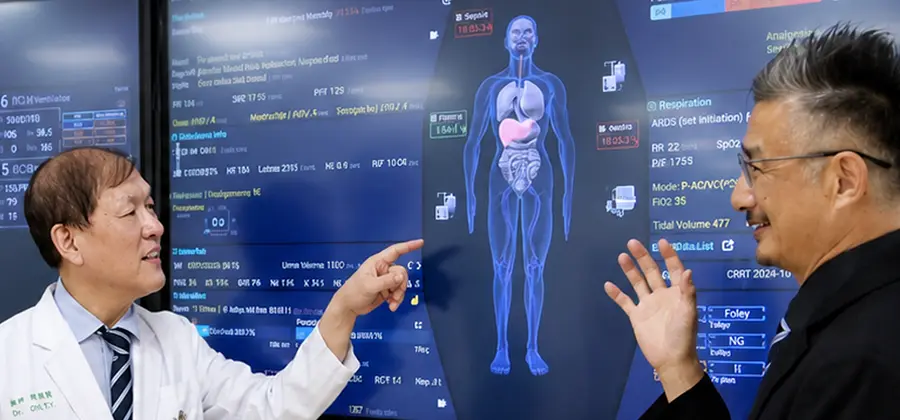
The iSEPS utilized artificial intelligence models and medical data to establish a predictive model for bacteremia. Through extensive data validation and interdisciplinary collaboration, the model has been successfully integrated into the hospital system. Its key features include:
iSEPS provides early warnings for bacteremia, aiding healthcare professionals in early identifying high-bacteremia risk patients and making timely treatment decisions. This enhances healthcare quality, reduces medication and healthcare costs, and improves patient outcomes.
The iSEPS model is versatile and can be applied and predicted in any hospital capable of producing cell population data. This means that other hospitals equipped with relevant instruments can also benefit from this research, thereby expanding its applicability.
With the integration of information, iSEPS need neither operation by medical staff, nor extra blood samples. This enhances clinical efficiency while reducing the burden on clinical personnel.
Real-World Deployment Validation (CMUH) The deployed model achieved an AUROC of 0.840, an AUPRC of 0.483, and an F1 score of 0.415.
Reduced Blood Culture Utilization Blood culture utilization decreased from 16.1% (8,565 patients) before implementation to 11.6% (6,070 patients) after implementation.
Improved Blood Culture Positivity Rate The positivity rate increased from 9.7% to 12.7%, indicating more targeted blood culture testing.
Accelerated Early Antibiotic Administration The proportion of patients receiving antibiotics within 3 hours increased from 20.4% to 22.3%, with greater improvements observed among patients with bacteremia and those undergoing blood culture testing.
Reduced Use of Multiple Intravenous Antibiotics Multiple intravenous antibiotic use decreased from 2.7% to 2.4% overall and from 2.1% to 1.6% among patients with normal white blood cell counts.
Reduced Hospitalization Among Patients with Normal White Blood Cell Counts Hospitalization rates decreased among patients with normal white blood cell counts without increasing emergency department revisit rates or revisit-related admissions.
The iSEPS relies on simpler data sources, requiring only complete blood count and cell population data. In contrast, other patents and studies incorporate additional biochemical markers, such as C-reactive protein and procalcitonin, as well as clinical parameters, increasing the complexity and cost of implementation.
The iSEPS demonstrates superior performance with an AUROC of 0.84, whereas the AUROC of other patents and studies ranges only from 0.802 to 0.814.
The iSEPS focuses on real-time application and clinical implementation. It has been successfully integrated into clinical information systems, providing immediate risk alerts and diagnostic assistance, making it suitable for emergency or time-critical clinical scenarios. In contrast, other patents and studies remain at the academic validation stage, lacking evidence of practical application.
Our team has published three peer-reviewed articles, with a fourth manuscript currently in preparation focusing on the clinical impact of iSEPS. A Taiwan patent was granted in May 2026. The project was also featured at the Taiwan Society of Emergency Medicine Annual Meeting through an invited presentation, highlighting its growing clinical and academic impact (see attached materials).
No additional blood samples are required.
Reduce unnecessary blood culture exam.
Early predict the risk of bacteremia.
Based on feedback from emergency physicians, nearly 90% agreed that the iSEPS:
Assists in prompting physicians to conduct infection-related examinations.
Aids in decision-making regarding the use of antibiotic treatment.
Provides timely prediction results.
Contributes to decision-making on patient disposition.
Features a concise and clear interface.
Exhibits overall excellent performance.
Smart Blood Test Meetings and Process Optimization: Regular multidisciplinary meetings are held every one to three months, involving hospital leadership, laboratory medicine, emergency medicine, information technology, and artificial intelligence teams. These meetings review project progress, discuss optimization strategies, evaluate clinical outcomes, and identify opportunities for workflow improvement and implementation.
Model Revision and Data Expansion: The model is updated every two to four quarters using newly collected data and clinical feedback. Continuous refinement focuses on improving predictive performance, robustness, and generalizability across diverse patient populations and clinical settings.
Last Model Update: Three-Tier Risk Stratification A single-threshold approach often creates a trade-off between sensitivity and false positives. To address this limitation, Version 3 introduces a Low–Medium–High risk stratification framework: * Low Risk (2.6%): Very low likelihood of bacteremia; unnecessary blood cultures and antibiotic use may be avoided. * Medium Risk (20.5%): Clinical assessment should guide further management. * High Risk (74.7%): High likelihood of bacteremia; prompt blood cultures and empiric antibiotic treatment should be considered. This approach provides more clinically actionable information than binary classification and supports more efficient use of diagnostic and treatment resources.
Risk Prediction for Bacteremia:
The model can quickly assess a patient’s risk of bacteremia by integrating complete blood count, white blood cell differential data, and cell population data, providing real-time predictive results to assist physicians with timely diagnostic support.
Antibiotic Treatment Decisions:
It provides guidance to physicians on whether to initiate intravenous antibiotics or second-line antibiotic treatment, reducing unnecessary antibiotic use and minimizing the risk of antibiotic resistance.
Recommendations for Infection-Related Examinations:
The model alerts physicians to perform further infection-related examinations, optimizing the use of laboratory and diagnostic resources.
Patient Disposition Decisions:
It assists clinicians in determining patient disposition, enhancing the efficiency of clinical resource utilization.