https://lmspiq.fda.gov.tw/web/DRPIQ/DRPIQ1000Result?licBaseId=225E2578-8875-468E-9346-E3956089AF7D
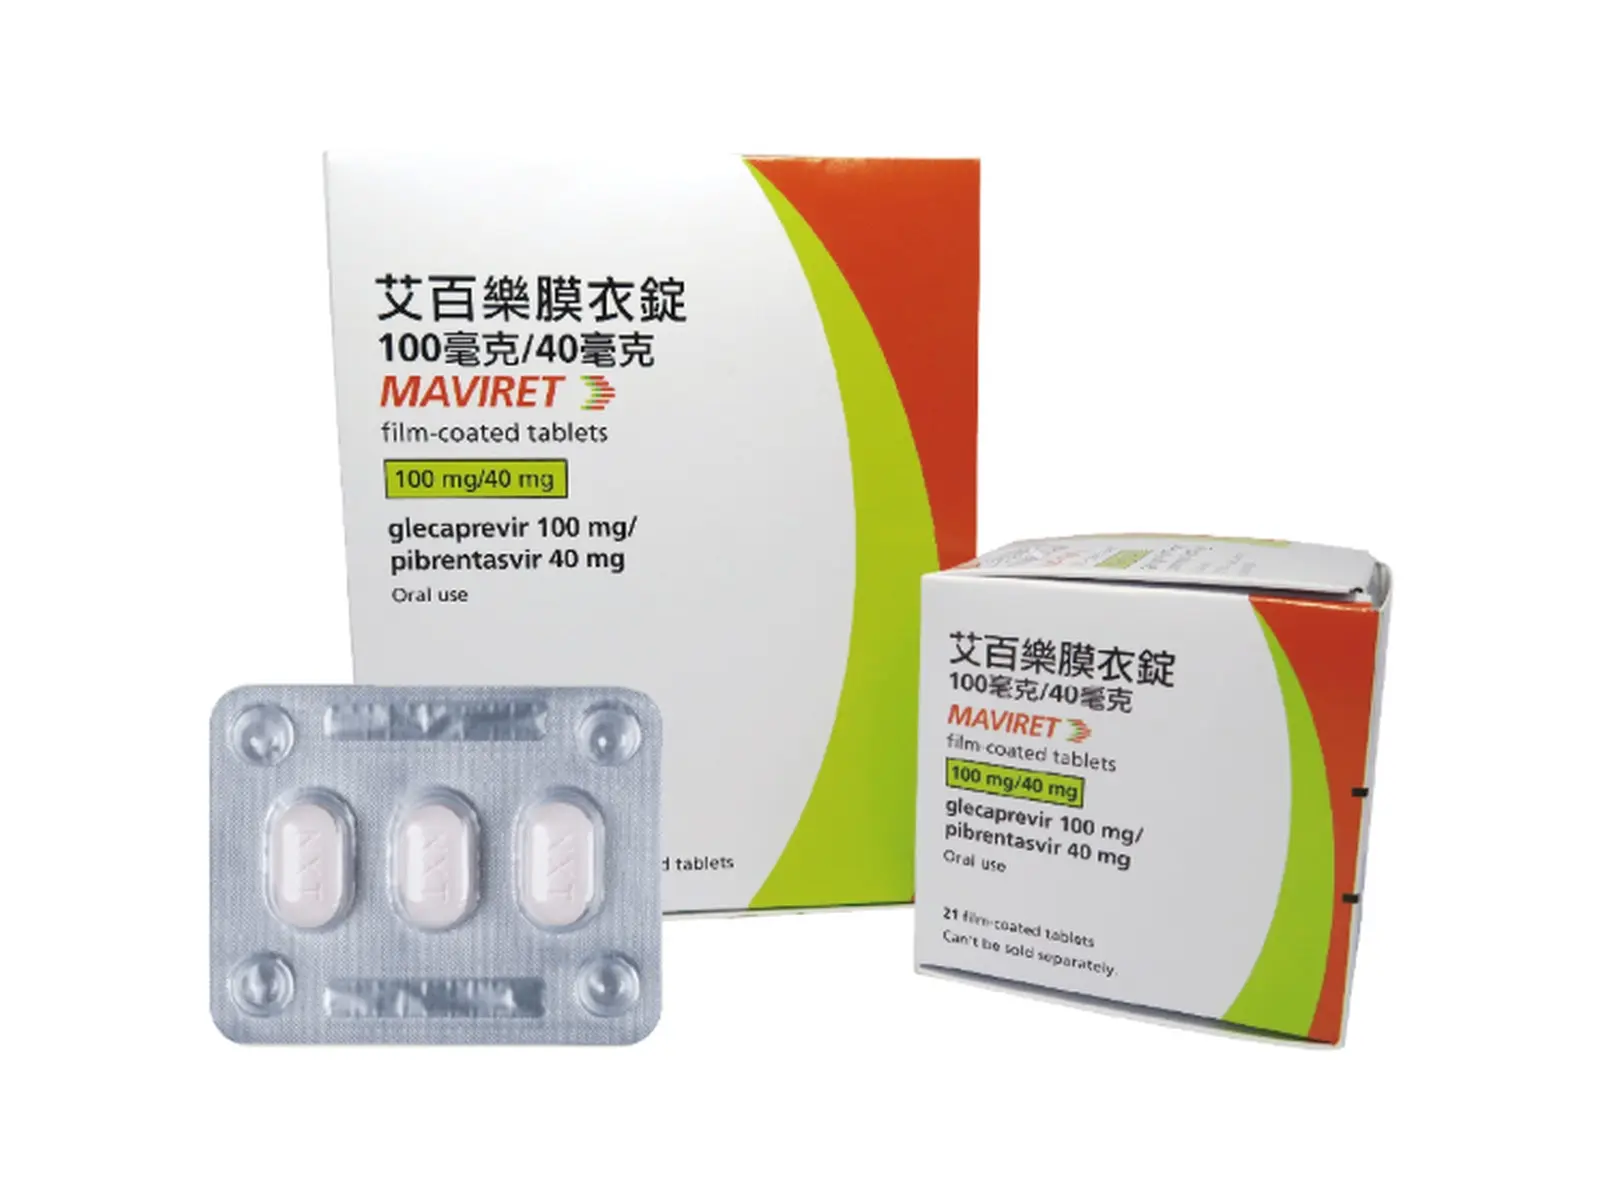
衛部藥輸字第027323號
有效日期:20250512
Fournier Laboratories Ireland Limited
1091060
GMP
Product verification covers active substance characterization, finished product formulation, film-coated tablet performance, dissolution, assay, impurities, stability, drug–drug interactions, renal impairment populations, and clinical efficacy and safety. The EMA assessment report describes finished product specifications including appearance, identification of glecaprevir and pibrentasvir, assay, uniformity of dosage units, degradation products, dissolution, water content, and microbiological quality. Process validation was planned on at least three commercial-scale batches, and batch data supported consistent quality and compliance with specifications. Stability verification included long-term, accelerated, photostability, temperature excursion, and temperature cycling studies, supporting product robustness without special storage conditions. Clinical verification used SVR12 as the key efficacy endpoint, while labeling incorporates risk information for HBV reactivation, hepatic function, drug interactions, and post-market safety monitoring.
QC implementation for Maviret is based on GxP requirements, approved specifications, ICH principles, and batch release controls. Incoming controls cover glecaprevir, pibrentasvir, excipients, coating materials, blister packaging, and outer packaging, supported by supplier qualification, material specifications, and testing records. Active substance specifications include appearance, identification, crystal form, particle size, assay, impurities, residual solvents, water content, microbiological quality, and relevant limit tests. In-process controls focus on blend uniformity, film-coated tablet formation, crystallinity/amorphous control, content uniformity, dissolution profile, and degradation product control. Finished product release testing includes appearance, HPLC/UV identification, assay, uniformity of dosage units, dissolution, water content, degradation products, and microbiological quality. EMA’s assessment notes that analytical methods were validated according to ICH guidelines and that a two-point dissolution specification was adopted to better control release of both active substances. Batch analysis data from commercial and intermediate-scale batches supported consistent quality, reinforcing the product’s fixed-dose convenience and stable clinical performance.
Maviret’s risk management system covers incoming materials, manufacturing, finished product release, logistics, clinical use, and post-market monitoring. Incoming risks are managed through supplier qualification, material specifications, batch documentation, and testing. Manufacturing risks are controlled through validated processes, critical quality attribute monitoring, deviation investigation, change control, and CAPA. Finished product risks are managed through COA review, approved specifications, batch record review, and stability data. EMA’s assessment also describes an ICH Q3D elemental impurity risk assessment supported by production-scale batch screening, with levels below the relevant control thresholds. Clinical risks are managed through labeling controls for HBV reactivation, hepatic decompensation/failure, contraindications, and drug–drug interactions. Before treatment, HBV testing, hepatic assessment, and concomitant medication review are recommended. Compared with older interferon/ribavirin-based regimens, Maviret provides an oral, fixed-dose, ribavirin-free, short-course, pan-genotypic treatment option, helping reduce treatment complexity and support patient access.
Post-market surveillance for Maviret is centered on pharmacovigilance, product quality complaint handling, signal detection, labeling updates, crisis response, and CAPA. The prescribing information includes clinical trial and post-approval safety information, including common adverse reactions such as headache, fatigue, and nausea, as well as postmarketing reports of angioedema and hepatic decompensation/failure. For key DAA-class risks, labeling requires testing for current or prior HBV infection before therapy and monitoring HCV/HBV coinfected patients for HBV reactivation and hepatitis flare during treatment and post-treatment follow-up. Risks related to hepatic impairment and contraindicated or not-recommended concomitant drugs such as atazanavir, rifampin, carbamazepine, efavirenz, and St. John’s wort are managed through labeling and healthcare professional education. Quality abnormalities or complaints should be documented, investigated, risk-assessed, reported where required, and addressed through corrective and preventive actions. As Maviret is a pharmaceutical product without embedded software, software maintenance or software update control is not applicable.
The advantages of Maviret® (glecaprevir/pibrentasvir, G/P) are supported by multiple peer-reviewed publications. Forns et al. reported the EXPEDITION-1 study in The Lancet Infectious Diseases, showing that once-daily G/P for 12 weeks achieved 99% SVR12 in patients with HCV genotypes 1, 2, 4, 5, or 6 and compensated cirrhosis, with a favorable safety profile, supporting treatment simplification. Asselah et al. published integrated Phase 3 results in Clinical Gastroenterology and Hepatology, demonstrating that 8-week G/P achieved SVR12 in at least 93% of non-cirrhotic patients with genotypes 2, 4, 5, or 6, with virologic failure below 1%. Wyles et al. reported data in Clinical Infectious Diseases supporting ribavirin-free G/P efficacy and safety in the historically more difficult-to-treat genotype 3 population. Brown et al. published EXPEDITION-8 in Journal of Hepatology, showing that 8-week G/P was well tolerated and achieved high SVR12 in treatment-naïve patients with GT1–6 infection and compensated cirrhosis. Rockstroh et al. further supported high efficacy and tolerability in HCV/HIV-1 co-infected patients. Overall, these publications support Maviret’s pan-genotypic, short-course, oral, ribavirin-free, once-daily profile and its utility across important patient subgroups.
Public patent records show that Maviret® (glecaprevir/pibrentasvir) is supported by patents covering fixed-dose combination therapy, treatment methods, solid dosage formulation, crystalline forms, and manufacturing processes. US10286029B2, “Method for treating HCV,” and US11484534B2, “Methods for treating HCV,” list AbbVie Inc. as assignee and relate to the use of glecaprevir/pibrentasvir-based antiviral combinations for HCV treatment, supporting the product’s pan-genotypic, ribavirin-free, short-course positioning. US11246866B2, “Solid pharmaceutical compositions for treating HCV,” relates to solid pharmaceutical compositions containing 100 mg glecaprevir and 40 mg pibrentasvir, including a bilayer amorphous solid dispersion design directly relevant to the fixed-dose film-coated tablet. US9321807B2, “Crystal forms,” and related patent families cover crystalline forms relevant to pibrentasvir quality and solid-state control. WO2020047182A1, “Process for manufacturing pibrentasvir active drug substance,” covers pibrentasvir drug substance, intermediates, compositions, and manufacturing processes designed to support low-impurity, commercial-scale production.